Type 1Preclinical development
LU-1001 / LU-1002
LU-1001 (injectable) is under investigation to assist CMD diagnosis.
LU-1002 (oral) is under investigation for maintenance therapy.

Lucier Pharmaceuticals
Lucier develops drug candidates targeting the unique mechanisms of coronary microvessels to treat endotype-specific coronary microvascular dysfunction (CMD).
Explore our scienceScience
Microvascular dysfunction can affect organs throughout the body, including the heart, eyes, and central nervous system. Lucier’s focus is coronary microvascular dysfunction, where effective, mechanism-directed therapies remain a significant unmet need.
Explore our programsThe microcirculation is a connected network of small arteries, arterioles, capillaries, and venules. These segments are distinguished by their size and function.
Our team focuses on coronary arterioles with an inner diameter of approximately 40–100 micrometers (µm) under maximal dilation. Definitions have evolved as research has revealed functional differences between arterioles and larger vessels around 200 µm in diameter.1
Microvascular autoregulation helps maintain adequate tissue perfusion over a range of arterial pressures. As pressure rises, arterioles constrict (narrow), limiting the pressure and flow transmitted downstream. As pressure falls, they dilate (widen), helping preserve blood flow. Within the autoregulatory range, this keeps tissue-level flow relatively stable when metabolic demand is unchanged.23 The interaction between small and large vessels also matters when CMD coexists with obstructive coronary artery disease.4
In 1988, Professor Lih Kuo and colleagues demonstrated pressure-dependent myogenic responses in isolated porcine coronary arterioles, establishing a foundation for understanding this intrinsic regulation of coronary blood flow.5
Human studies after coronary intervention help explain how blood flow and microvascular resistance adapt when upstream coronary disease is treated, and how coexisting CMD can affect symptoms.234 In a 2026 study, resting blood flow remained stable because microvascular resistance increased as epicardial resistance fell, providing direct evidence of coronary autoregulation in humans.6
Coronary microvascular dysfunction (CMD) affects the regulation of blood flow in the heart’s small vessels. It can contribute to angina, ischemia, or myocardial infarction, including when the large coronary arteries are not obstructed.7
ANOCA, INOCA, and MINOCA describe clinical presentations; CMD can be an underlying mechanism, but these terms are not interchangeable with CMD and may have other causes.7
Four dedicated U.S. ICD-10-CM codes recognize CMD: I20.81 (angina with CMD), I21.B (myocardial infarction with CMD), I24.81 (acute CMD), and I25.85 (chronic CMD).8
A systematic review and meta-analysis of 56 studies involving 14,427 patients estimated a pooled CMD prevalence of 41% (95% confidence interval, 36–47%) among patients with no obstructive coronary artery disease.9
That estimate applies to the populations studied, rather than the general population. CMD can also coexist with disease in larger coronary arteries, so a focus on nonobstructive disease alone does not capture its full clinical reach. Greater access to coronary physiology assessment can help reveal these distinct mechanisms.4
Pipeline
Type 1Preclinical development
LU-1001 (injectable) is under investigation to assist CMD diagnosis.
LU-1002 (oral) is under investigation for maintenance therapy.
Type 2Potential late-phase development
An undisclosed asset being evaluated for a specific CMD subtype, with a focus on CMD endotyping and endotype-specific therapy.
All programs are investigational. Safety and efficacy for CMD have not been established, and no Lucier candidate is approved for patient use.
LU-1001 / LU-1002 mechanism
Endothelin-1 (ET‑1) binds to the ET‑A receptor on the smooth muscle cell, initiating signaling
inside the cell.
Research
Explore the clinical observations and experimental research informing our approach to CMD.
From the first clinical observations to shared terminology and dedicated diagnostic codes.
Signs of coronary heart disease despite apparently normal angiograms.
Original NEJM report (opens in a new tab)Dr. Richard O. Cannon III reviews the continuing challenge of chest pain with normal coronary angiograms, historically described as cardiac syndrome X. The review examines microvascular angina and unresolved questions about its mechanisms, diagnosis, and treatment.
Cannon’s historical review (opens in a new tab)Crea, Camici, and Bairey Merz review four clinical settings: CMD without myocardial disease or obstructive coronary artery disease; CMD with myocardial disease; CMD with obstructive coronary artery disease; and iatrogenic CMD. These clinical categories provide context for the diverse mechanisms underlying CMD.
CMD classification review (opens in a new tab)Four U.S. ICD-10-CM codes recognize CMD: I20.81, I21.B, I24.81 and I25.85.
ICD-10-CM update (opens in a new tab)A persistent treatment-evidence gap. The trials below did not establish benefit on their primary outcomes; their populations, treatments, and endpoints differ. These results reinforce the need to understand CMD mechanisms and develop therapies directed at them.
This pilot trial found no significant improvement in angina frequency or invasive microvascular function versus placebo at three months.
NCT02147067Trial publication (opens in a new tab)Diltiazem did not substantially improve the primary coronary-function endpoint, symptoms, or quality of life over six weeks, although epicardial spasm was reduced.
NCT04777045Trial publication (opens in a new tab)The primary exercise-duration endpoint did not improve versus placebo. Adverse events were more common with zibotentan.
NCT04097314Trial publication (opens in a new tab)No significant difference in the primary cardiovascular-event endpoint was found in women with suspected INOCA. Enrollment shortfalls and treatment crossover limit interpretation.
NCT03417388ACC trial report (opens in a new tab)Vericiguat did not demonstrate improved peripheral vasodilator function or anginal symptoms in patients with coronary vasospasm during this crossover trial.
NCT06415227Trial publication (opens in a new tab)Study investigators presented data and concluded that “Although CSR implantation was safe, the data showed no significant improvement in CMR perfusion metrics, symptoms or quality of life compared with a sham procedures in these patients, who currently have no other evidence-based treatment options.”
NCT05492110 trial registration (opens in a new tab)ACC trial report (opens in a new tab)Lucier’s work builds on direct study of coronary arterioles. Understanding their distinct behavior helps us challenge assumptions drawn from larger vessels and investigate mechanisms that may enable endotype-specific medicines.
Dr. Lih Kuo and colleagues demonstrate pressure-dependent myogenic activity in isolated porcine coronary arterioles, supporting a role in blood-flow autoregulation.
Read the study (opens in a new tab)In isolated porcine coronary microvessels, adenosine dilated the smallest arterioles at the lowest concentrations, with larger vessels requiring higher concentrations. The endothelium-independent dilator nitroprusside produced similar responses across vessel sizes, while larger arterioles responded more strongly to flow-induced shear stress. These findings show why vessel size and the stimulus both matter.
Read the study (opens in a new tab)Pries and Reglin identify a decline in experimental studies of coronary microvessels, despite growing clinical research, as a potential barrier to progress. They argue that understanding disease mechanisms is essential to classify CMD, guide diagnosis, and identify therapeutic targets. The review calls for relevant animal models, improved experimental methods, and scientific meetings to close this gap.
Read the black-box review (opens in a new tab)An ACC-led working group outlines the knowledge gaps in INOCA and the research needed to develop evidence-based therapies. It calls for a better understanding of underlying mechanisms and a coordinated approach to future studies.
Read the research agenda (opens in a new tab)In a mouse model of pressure-overload hypertrophy, acetylcholine causes coronary arteriolar constriction despite an intact endothelium. The findings implicate elevated Rho kinase activity in microvascular dysfunction.
Read the study (opens in a new tab)Direct coronary physiology measurements show that changes in microvascular resistance help maintain stable resting blood flow as resistance in the large coronary arteries changes, providing evidence of autoregulation in humans.
Read the study (opens in a new tab)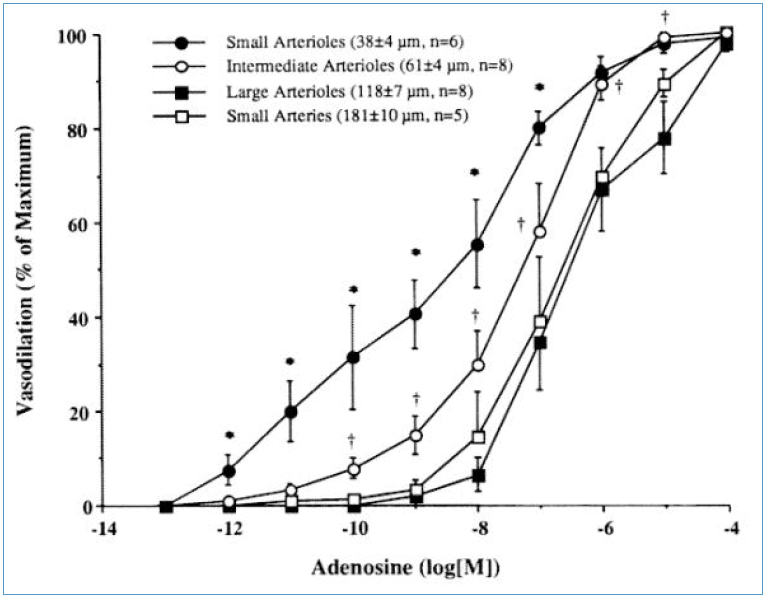
Figure 1
Adenosine dilates coronary microvessels and is commonly used during coronary physiology assessment to measure coronary flow reserve and microvascular resistance. An impaired flow response can help identify CMD.7
Dr. Lih Kuo and colleagues showed that small coronary arterioles were more sensitive to adenosine than larger microvascular segments. The curves shift to higher concentrations as vessel size increases, demonstrating distinct responses along the coronary microcirculation.1
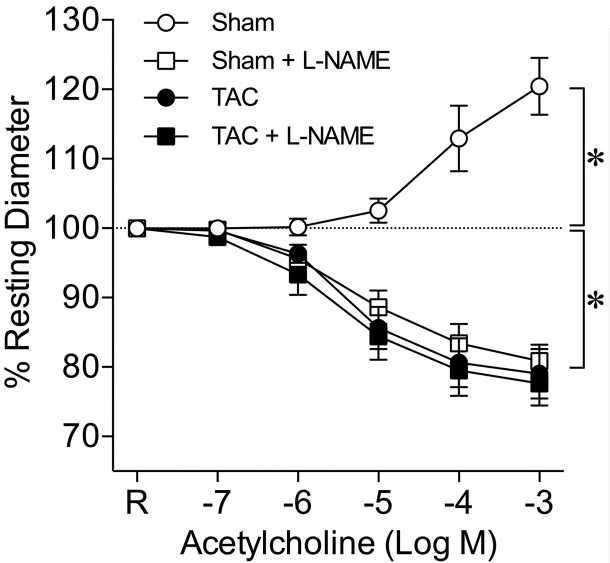
Figure 2
Acetylcholine (ACh) can cause paradoxical vasoconstriction in diseased coronary arterioles even when the endothelium remains intact.10 In clinical practice, acetylcholine provocation testing helps assess epicardial coronary spasm and microvascular spasm.7
The team observed ACh-induced constriction in coronary arterioles isolated from pressure-overload mice. Elevated Rho kinase activity was implicated in the abnormal response, and inhibiting Rho kinase abolished the ACh-induced constriction. These experimental findings support further investigation of this pathway in CMD.10
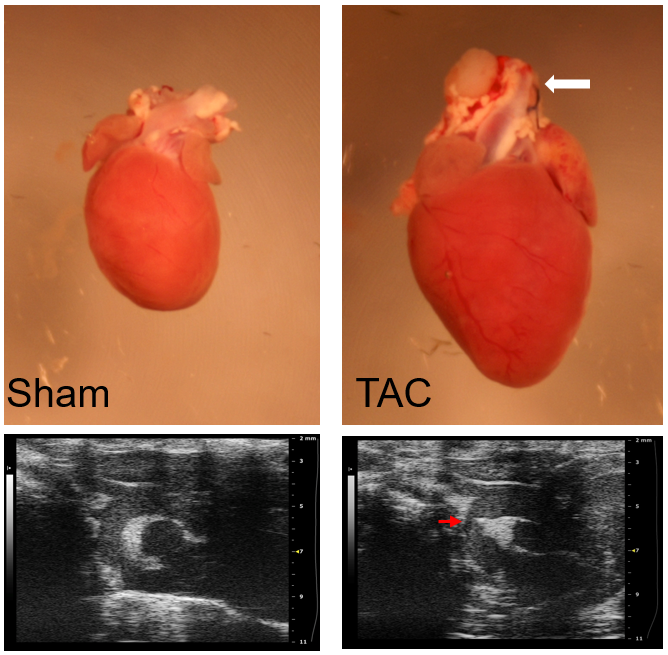
Figure 3
The paradoxical response shown in Figure 2 was observed in coronary arterioles isolated from a pressure-overload mouse model. Narrowing the aorta by transverse aortic constriction (TAC) increased the heart’s workload and produced cardiac hypertrophy.10
The upper panels compare a sham-control heart with an enlarged TAC heart. The lower panels show corresponding ultrasound images of the aorta. This model linked altered arteriolar responses with impaired coronary flow regulation and cardiac function; it does not represent every form of human CMD.10
Team
Lucier’s programs draw on coronary arteriolar research originating at Texas A&M University (patent publication PCT/US2024/029067; opens in a new tab). Our advisors bring experience in vascular biology, translational research, preclinical development, and biotechnology strategy.

MD, MBA
Founder, President and CEO
Co-inventor

PhD
Scientific Advisor
Co-inventor; Regents Professor

MD
Business Advisor
Investor and Entrepreneur

Preclinical Development Advisor
Registered Toxicologist

MD, PhD
KOL interventional cardiologist
Baylor Scott & White Health
Contact
For investment, research, clinical collaboration, and drug development.
Get in touch